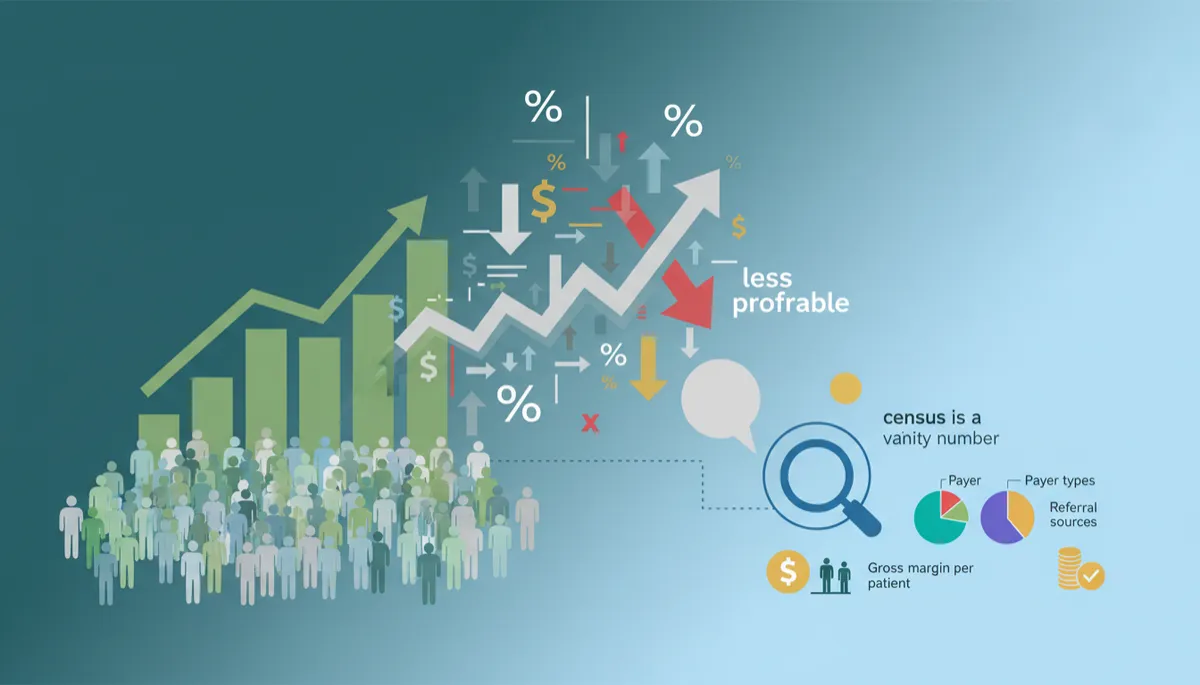
Growing Census: Impact on Home Health Profitability
Home Health, Profitability, Operations
Why Growing Census Can Quietly Make You Less Profitable
More patients should mean more revenue. Yet many agencies discover that as their census climbs, their bank balance doesn’t. Understanding why growth can erode margin is the first step to scaling in a way that actually strengthens your bottom line.
More Patients, Not Always More Profit
See beyond census to protect your margins
When More Patients Don’t Mean More Profit
On paper, the logic is simple: more patients = more visits = more revenue. But in reality, growth in census doesn’t automatically translate into increased profit. In fact, it can quietly shrink your margin if you’re not watching the right numbers.
As census grows, your team’s time stretches, scheduling gets messier, and your case mix shifts. You may be adding patients who are harder to staff, lower reimbursing, or more complex to manage. Revenue goes up, but cost per dollar of revenue can climb even faster. That’s how agencies end up working harder, serving more patients, and taking home less profit.
Marginal Patients Aren’t Always Marginal Wins
Many leaders assume that once fixed costs are covered, every additional patient is a “marginal win” that adds almost pure profit. That’s only true if the incremental revenue from each new patient meaningfully exceeds the incremental cost of serving them.
Consider the “last” few patients you accept in a week:
They may live farther away, driving up travel time and mileage.
They may be covered by lower-paying payers with strict utilization management.
They may require more coordination, phone calls, and documentation per visit.
Those “marginal” patients can actually be margin negative. They consume scarce clinician time and scheduling capacity that could have gone to higher-margin cases. Without visibility into patient-level economics, it’s easy to celebrate growth that is quietly diluting profit.
Fixed Overhead Doesn’t Explain the Whole Story
It’s common to hear, “Our overhead is fixed, so once we cover it, growth is all upside.” That’s only partly true. Yes, rent, software, and some administrative salaries are relatively fixed. But as census grows, many “fixed” costs start behaving like variable or step costs.
You add another scheduler or clinical supervisor to keep up with volume.
Overtime and per-visit pay creep up when staffing gets tight.
Turnover rises, introducing recruiting and orientation costs that don’t show up as a neat line item.
If you only look at total overhead spread across total visits, you miss where growth is forcing new layers of cost into the business. That’s why “we just need more census” can be a dangerous oversimplification.

Segmenting margin by payer and referral source reveals which growth truly pays.
Case Mix Complexity Compounds Quietly
As you grow, your case mix almost always changes. You may take on sicker patients, more behavioral health needs, or families who require extra education and support. Each of these factors increases the time and cognitive load per patient, even if the reimbursement doesn’t keep pace.
Complexity compounds in subtle ways:
More coordination with physicians and payers.
Higher risk of rescheduled or missed visits that disrupt routes.
Longer documentation time per encounter.
None of this shows up in your census count. But it directly affects how many patients each clinician can realistically and safely manage—and therefore how profitable your “bigger” census really is.
What to Actually Measure: Margin by Payer and Referral Source
To move beyond vanity metrics, you need to measure what truly drives financial health. A powerful starting point is tracking gross margin per patient by:
Payer type (Medicare, Medicaid, commercial, managed care, self-pay, etc.).
Referral source (specific hospitals, physicians, facilities, or partners).
Gross margin per patient forces you to combine revenue and direct costs into a single, comparable number. When you slice that by payer and by referral source, patterns emerge quickly:
Some referral partners send high-volume, low-margin patients that strain your team.
Others deliver fewer patients, but each one is solidly profitable and easier to staff.
Once you can see this clearly, you can make deliberate choices about where to invest growth efforts, renegotiate rates, or reset expectations with certain partners.
Census Is a Vanity Number Until It’s Paired with Margin
Census alone is a vanity metric. It’s easy to track, easy to celebrate, and easy to compare. But without a margin lens, it can be dangerously misleading. A census of 150 patients with thin or negative margins is far worse than a census of 90 patients with strong, predictable margins.
The real power comes from pairing census with gross margin per patient. That tells you:
How profitable your current book of business truly is.
Whether adding more patients like the ones you have will help or hurt.
Until you connect these two metrics, “growth” is just a bigger number on a census report—not necessarily a healthier agency.
Focus Growth on Your Most Profitable Segments
Once you know your gross margin per patient by payer and referral source, you can shift from “grow at all costs” to grow where it counts. That means:
Deepening relationships with referral sources that send high-margin, appropriately complex patients.
Being more selective—or renegotiating terms—with consistently unprofitable payers or partners.
Designing staffing models and care pathways around the segments that truly sustain your agency.
Growth then becomes intentional: not “How do we add 20 more patients?” but “How do we add 20 more of the right patients?” That’s the shift from chasing census to building a resilient, profitable agency that can keep serving your community for the long term.


